


Safe laxatives during pregnancy range from bulk-forming fiber to osmotic laxatives such as polyethylene glycol, often tried first when diet, fluids, and movement aren’t enough, with stool softeners and stimulant laxatives generally reserved for when those steps haven’t worked or a provider is directing your care. Constipation is one of the most common gastrointestinal complaints in pregnancy, with estimates ranging from about 11% to 38% depending on how it’s measured [1][2], and iron supplementation linked to meaningfully higher odds of the problem [2].
This guide breaks down what the research and major medical organizations say about each category, and which options are generally reserved for a doctor’s direct guidance rather than self-treatment. As with anything you take during pregnancy, it’s meant to help you have an informed conversation with your OB-GYN or midwife, not replace one.
Why Pregnancy Causes Constipation in the First Place
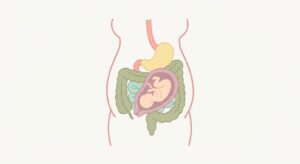
Before choosing a laxative, it helps to understand what is actually happening. Rising progesterone relaxes smooth muscle throughout the body, including the muscle lining the intestines, which slows the movement of stool through the colon. Later in pregnancy, the growing uterus adds physical pressure on the bowel, and prenatal iron supplements are well known to have a constipating effect for many women. Reduced activity and inadequate fluid intake often compound the problem [1].
Because of this mix of causes, most obstetric guidance recommends starting with non-drug approaches: more dietary fiber, more water, and regular movement, before reaching for a laxative at all. A 2022 cohort study found that women with both low fiber and low fluid intake had substantially higher odds of constipation than women who got enough of both [3], which is one reason lifestyle changes are consistently positioned as step one rather than an afterthought.
Our guide on high-fiber foods for pregnancy constipation relief covers this first-line approach in detail, and our piece on dehydration and constipation explains why fluid intake matters just as much as fiber does.
When those measures are not quite enough, here is how the main categories of laxatives compare.
Bulk-Forming Fiber Laxatives: Often the First Medication Considered
Bulk-forming laxatives, such as psyllium (Metamucil) and polycarbophil (FiberCon), work by absorbing water in the gut to add soft bulk to the stool, which then triggers the bowel’s natural stretch reflex. Because they are not absorbed into the bloodstream in any meaningful amount, they are widely considered one of the safer options to start with during pregnancy, and are often a commonly used first option in pregnancy guidance [6].
That said, fiber supplements need to be taken with enough water. Without it, they can occasionally make constipation feel worse rather than better, since the fiber swells but has nothing to move it along. If you take a fiber supplement with prenatal vitamins or iron, ask your pharmacist or OB-GYN whether you should separate the doses. If you are deciding between products, our comparison of MiraLAX vs Metamucil looks at how a fiber-based approach stacks up against an osmotic one for pregnancy-related constipation specifically.
If you’re choosing a specific psyllium product, options include NOW Foods Psyllium Husk Caps 500mg (taken with a full glass of water per dose) or Metamucil 4-in-1 Sugar-Free Fiber Powder; confirm dosing with your OB-GYN before starting either one.

Osmotic Laxatives: Common Options During Pregnancy
Osmotic laxatives work by drawing water into the intestines rather than being absorbed by the body, which is part of why they tend to be viewed favorably in pregnancy. This category includes three products that come up most often:
- Polyethylene glycol (PEG 3350), sold as MiraLAX: Polyethylene glycol is minimally absorbed from the gastrointestinal tract and is generally considered a low-exposure option during pregnancy [5][13]. A randomized, placebo-controlled, multicenter trial of PEG 3350 in adults with chronic constipation found it significantly improved stool frequency and consistency compared with placebo [4], though that trial was not conducted in pregnant women; its relevance to pregnancy comes from PEG’s general pharmacokinetic profile rather than from the trial itself.
- Magnesium hydroxide (Milk of Magnesia) and other magnesium-containing osmotic laxatives: These may be used during pregnancy when recommended by a healthcare professional. Regular or high-dose use can cause diarrhea, cramping, or electrolyte problems, and people with kidney disease need particular caution [5][13].
- Lactulose: Generally considered an option during pregnancy, although it can cause gas, bloating, and abdominal cramping for some people [5].
Worth flagging separately: high-dose magnesium “cleanse” style products, such as Mag O7 or Oxy-Powder, use much larger doses of magnesium than a typical Milk of Magnesia serving and have not been specifically studied in pregnant populations. These are generally something to avoid self-dosing during pregnancy without your provider’s direct sign-off, a point our own reviews of Mag O7 and Oxy-Powder also make.
For a closer look at how PEG compares with a saline option, our guide on Bisacodyl vs Milk of Magnesia vs MiraLax breaks down onset time and side effects for each.
Stool Softeners: Helpful, With One Caution Worth Knowing
Docusate sodium (Colace) and docusate calcium (Surfak) are stool softeners rather than true laxatives. They work by helping water mix into the stool so it is easier to pass, without stimulating the bowel directly. Because only a small amount of docusate is absorbed systemically, it has been commonly used during pregnancy, although current guidance generally places bulk-forming and osmotic options earlier in the treatment approach [6][12].
There is one specific safety note worth being transparent about. A single published case report from 1984 described a newborn with low blood magnesium (hypomagnesemia) after the mother had taken docusate in higher-than-recommended amounts throughout her pregnancy; the mother’s own magnesium levels normalized once she stopped the docusate [7][8].
This appears to be an isolated case tied to chronic overuse rather than typical short-term, recommended-dose use. Available observational data have not shown an increased risk of birth defects with recommended docusate use [8].
This is one reason it is important to use docusate only as directed and discuss ongoing use with your healthcare provider. Our guide to the best stool softeners for constipation covers dosing and other considerations in more depth, and if you are wondering about combining approaches, see can you take MiraLAX and Colace together.
Stimulant Laxatives: Usually Used After Other Options
Stimulant laxatives, including bisacodyl (Dulcolax) and senna, work by directly triggering muscle contractions in the colon wall. They tend to be effective and fast-acting, but they are generally considered only after other options have not been sufficient or when a healthcare professional recommends them, in part because they can cause more abdominal cramping [9][12][13].
Bisacodyl is generally considered an option when other approaches have not been sufficient, but it can cause abdominal cramping and should be used according to product directions and, during pregnancy, with guidance from a healthcare professional. Most sources describe bisacodyl specifically as having low systemic absorption [9][13].
Senna deserves a more specific note. It is a stimulant laxative whether it comes as a tea or a tablet, and it can cause abdominal cramping. Senna has not been shown to cause harm in pregnancy, but stimulant laxatives are generally considered after bulk-forming and osmotic options [12].
If you are pregnant, it is best to check with your pharmacist or OB-GYN before using senna rather than assuming it is interchangeable with fiber or osmotic options. Senna metabolites also pass into breast milk in small amounts, with effects on nursing infants not well studied [12]. Our guide on senna tea for constipation goes into this in more detail.
Probiotics: A Possible Supporting Option
Probiotics are not laxatives, but some pregnancy-specific studies have explored their role in constipation, including a small pilot study of a multispecies probiotic blend that found improved bowel movement frequency over four weeks with no reported adverse effects on mother or baby [10], and a larger systematic review of probiotic and prebiotic safety in pregnancy and lactation that likewise did not find evidence of increased adverse effects [11].
The evidence base here remains limited, so probiotics are best considered a supportive dietary option alongside fiber and fluids, rather than a substitute for established constipation treatments. Our dedicated guide on safe probiotics for pregnancy-related constipation reviews specific strains and products.
What Is Generally Not Recommended During Pregnancy
- Castor oil: It can cause intestinal cramping and diarrhea and is sometimes used in attempts to stimulate labor. It’s generally best avoided as a self-directed constipation treatment during pregnancy; discuss it with your provider first if it comes up.
- Mineral oil (taken orally, therapeutically): Can interfere with the absorption of certain vitamins with regular use, so it’s generally best used only under medical guidance during pregnancy rather than self-directed [6][13].
- Any laxative used long-term without medical guidance: If constipation persists, repeated or long-term laxative use should be discussed with your healthcare provider rather than managed indefinitely on your own.
A Special Case: Constipation From Iron Supplements
If your constipation started or worsened right after you began prenatal vitamins, iron is a very common culprit. Rather than only adding a laxative on top, it is worth discussing the iron itself with your provider — if constipation began after starting an iron supplement, ask your provider whether the dose, formulation, or timing can be adjusted. Our full guide on the best laxative for constipation from iron pills walks through this specific situation.
Does It Matter Which Trimester You Are In?
For commonly used options such as bulk-forming fiber and osmotic laxatives, guidance generally focuses more on the type of laxative, dose, duration, and the individual pregnancy than on a specific trimester cutoff. That said, a few general patterns are worth knowing:
- Second and third trimester: Constipation may become more noticeable later in pregnancy as hormonal changes and the growing uterus affect bowel function.
- Any trimester: If you are also managing iron supplementation, constipation risk tends to stay elevated throughout, which is why the iron-specific guide above is worth reading regardless of how far along you are.
When to Contact Your Doctor Instead of Self-Treating
Reach out to your OB-GYN or midwife promptly, rather than trying another over-the-counter product first, if you notice any of the following:
- Severe abdominal pain or cramping
- Blood in the stool or rectal bleeding
- Constipation that has lasted more than two weeks despite dietary changes
- Persistent constipation that repeatedly alternates with diarrhea
- Nausea and vomiting alongside the constipation, which can occasionally point to a bowel obstruction
- No improvement despite following your provider’s advice or the product directions for a reasonable first-line approach
Frequently Asked Questions
What is the safest laxative to take during pregnancy?
There is no single laxative that is safest for every pregnancy. Bulk-forming fiber such as psyllium is often considered a first option, while osmotic laxatives such as polyethylene glycol may be considered when additional treatment is needed. Always confirm the choice with your own OB-GYN or midwife before starting.
Is it safe to take MiraLAX every day while pregnant?
MiraLAX contains polyethylene glycol 3350, which has minimal systemic absorption and is commonly considered an option when needed, with clinician guidance, rather than something to use routinely on your own. If you find you need it regularly or for longer-term use, discuss the plan with your OB-GYN or midwife.
Can I take a stool softener like Colace throughout my pregnancy?
Docusate (Colace) is commonly used in pregnancy at recommended doses. The main caution in the literature is a single case report tied to chronic overuse leading to low newborn magnesium, not typical short-term or as-directed use. Occasional or short-term use under your provider’s guidance is generally viewed differently than continuous daily use for months without medical follow-up.
Are natural laxatives, like senna tea, safer than pharmacy laxatives during pregnancy?
Not necessarily. Senna is a stimulant laxative whether it comes as a tea or a tablet. Because treatment choices during pregnancy depend on the specific product, dose, duration, and individual circumstances, it is worth checking with your provider or pharmacist before using senna rather than assuming that “natural” automatically means lower-risk.
Can laxative use during pregnancy affect the baby?
Available pregnancy data are generally reassuring when commonly used laxatives are taken at recommended doses, although research is limited for some individual products. Bulk-forming fiber and osmotic laxatives such as polyethylene glycol have low systemic absorption, while stimulant laxatives can cause abdominal cramping. Using laxatives in excessive amounts or for prolonged periods can cause problems such as electrolyte disturbances, so discuss regular or prolonged use with your OB-GYN or midwife.
Quick Reference: Laxative Categories in Pregnancy
| Category | Examples | General Standing in Pregnancy |
|---|---|---|
| Bulk-forming fiber | Psyllium (Metamucil), polycarbophil (FiberCon) | Typically first-line; take with plenty of water |
| Osmotic | PEG 3350 (MiraLAX), magnesium hydroxide, lactulose | Commonly used options include PEG 3350 and lactulose; choice depends on the individual |
| Stool softener | Docusate (Colace, Surfak) | Commonly used in pregnancy; prolonged or high-dose use should be discussed with a healthcare provider |
| Stimulant | Bisacodyl (Dulcolax), senna | Generally reserved for when other options fail; check with your pharmacist or OB-GYN before use, especially for senna |
| Best avoided without guidance | Castor oil, therapeutic mineral oil | Generally avoided as a self-directed remedy in pregnancy; discuss with your provider first |
The Bottom Line
For most pregnant women, a reasonable approach starts with diet, hydration, and movement, moves next to a bulk-forming fiber supplement or an osmotic laxative like PEG if needed, and reserves stimulant laxatives for situations your provider is actively guiding. None of the categories discussed here are risk-free in every circumstance, which is exactly why “safe” always comes with the qualifier “at recommended doses, and ideally with your OB-GYN or midwife in the loop.”
For a broader, medication-free starting point, see our guides on high-fiber foods for pregnancy constipation and fast constipation relief at home, and if a full comparison of every OTC option would help, our roundup of the best OTC laxatives for constipation covers the non-pregnancy population alongside pregnancy-specific notes.
References
- Vazquez JC. Constipation, haemorrhoids, and heartburn in pregnancy. BMJ Clin Evid. 2010;2010:1411. Link
- Bradley CS, Kennedy CM, Turcea AM, Rao SS, Nygaard IE. Constipation in pregnancy: prevalence, symptoms, and risk factors. Obstet Gynecol. 2007;110(6):1351-1357. Link
- Reijonen JK, Tihtonen KMH, Luukkaala TH, Uotila JT. Association of dietary fiber, liquid intake and lifestyle characteristics with gastrointestinal symptoms and pregnancy outcome. European Journal of Obstetrics & Gynecology and Reproductive Biology: X. 2022;16:100168. Link
- DiPalma JA, DeRidder PH, Orlando RC, Kolts BE, Cleveland MB. A randomized, placebo-controlled, multicenter study of the safety and efficacy of a new polyethylene glycol laxative. Am J Gastroenterol. 2000;95(2):446-450. Link
- Mayo Clinic. Pregnancy constipation: Are stool softeners safe? Link
- American Family Physician (AAFP). Over-the-Counter Medications in Pregnancy. October 2023. Link
- Schindler AM. Isolated neonatal hypomagnesaemia associated with maternal overuse of stool softener. Lancet. 1984;2:822.
- MotherToBaby (OTIS). Docusate Sodium Fact Sheet, January 2025. Link
- Pharmacy Times. A Pharmacist’s Guide to Managing Constipation in Pregnancy. Link
- de Milliano I, Tabbers MM, van der Post JA, Benninga MA. Is a multispecies probiotic mixture effective in constipation during pregnancy? A pilot study. Nutrition Journal. 2012;11:80. Link
- Sheyholislami H, Connor KL. Are Probiotics and Prebiotics Safe for Use during Pregnancy and Lactation? A Systematic Review and Meta-Analysis. Nutrients. 2021;13(7):2382. Link
- Medicines in Pregnancy (UK Teratology Information Service patient leaflet). Senna. Link
- MotherToBaby (OTIS). Laxatives Fact Sheet. April 1, 2026. Link
ConstipationRelief.net is reader-supported. We may earn a commission from purchases made through the Amazon links in this article, at no extra cost to you. We aim to provide evidence-based information and clearly distinguish general product information from pregnancy-specific safety evidence.
This article is intended for informational and educational purposes only and does not constitute medical advice. Always consult your OB-GYN, midwife, or a qualified healthcare provider before starting, stopping, or changing any laxative, fiber supplement, or probiotic during pregnancy.




